
By Aleksander Wiecki · Chief Marketing Officer, IVF Media · Vice-Chair, European Fertility Society
Published: October 2026 · Data: IVF Failure & Clinic Switching Survey (IVF Media, 2025) · Sample: 611 patients, 59 countries
A failed IVF cycle is one of the hardest moments in fertility treatment. And it’s far more common than clinic brochures suggest.
So we asked the people who’ve lived through it. IVF Media’s IVF Failure & Clinic Switching Survey gathered answers from 611 patients in 59 countries who’d had at least one IVF cycle that didn’t work. We asked how many cycles they’d been through, whether they changed clinic, why, what it had cost them so far – and whether they’d go abroad for their next attempt. It builds on our earlier IVF Abroad Patient Research, a survey of 1,189 patients looking for treatment abroad.
The answers tell a clear story. Failure is common. Patience with clinics is short. Costs at home are crushing. And a large majority are ready to look across the border.
This article walks through every finding, country by country. If you’re reading it after your own failed cycle, you’ll find two things here: proof that you’re not alone, and practical guidance on what to do next.
Key findings at a glance
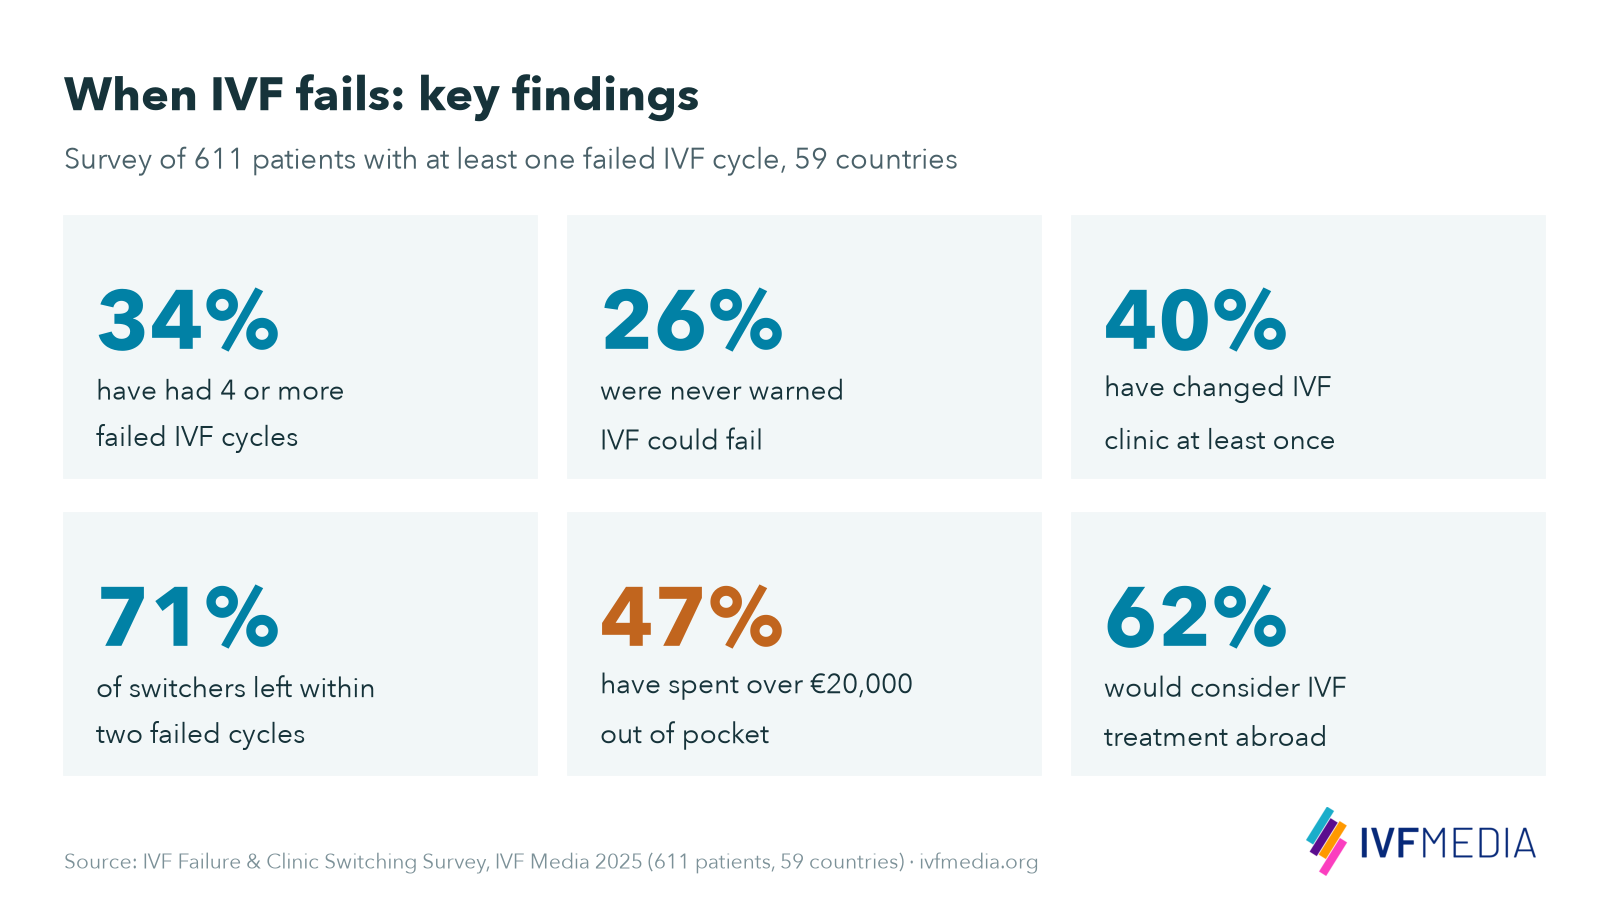
- One in three patients (34%) has been through four or more failed IVF cycles. Half (50%) have had three or more.
- One in four patients (26%) says no doctor warned them IVF could fail before treatment began.
- 40% of patients have changed IVF clinic at least once. Among patients with four or more failed cycles, 69% have used two or more clinics.
- Patients leave fast. 41% of clinic-switchers left after just one failed cycle. 71% left within two.
- It’s not only about results. A disappointing outcome drove 57% of switches – but poor communication (38%) and a broken relationship with the doctor (36%) together featured in 51%. Cost drove only 11%.
- 47% of patients have spent more than €20,000 out of their own pocket on IVF. In the US, it’s 59%.
- 62% would consider IVF treatment abroad. That rises to 80% in Germany, 75% in the UK and 73% in Ireland – and to 81% among patients aged 45 and over.
- One in five (20%) had their most recent cycle abroad already – mainly in Greece, Spain and the Czech Republic. 96% of them would consider going abroad again.
- The budget paradox: patients who’ve spent €20,000+ at home mostly plan to spend far less abroad. 56% of patients open to treatment abroad budget under €9,000.
- The main barrier to going abroad is the trip, not the treatment. 76% of patients who wouldn’t go abroad cite travel costs and logistics. Only 20% cite the cost of treatment itself.
Who took part in this research?
611 patients took part, all with at least one IVF cycle behind them. They came from 59 countries.
The biggest groups were patients living in:
| Country of residence | Share of sample |
|---|---|
| United States | 39% |
| United Kingdom | 18% |
| Ireland | 7% |
| Canada | 6% |
| Australia | 5% |
| Germany | 4% |
| 53 other countries | 21% |
The “other countries” group includes patients from Sweden, Switzerland, South Africa, the Netherlands, Spain, India, Portugal and dozens more.
Age: the average patient was 38.9 years old (median 39). Two in three (67%) were between 35 and 44. The youngest was 24, the oldest 67.
| Age group | Share |
|---|---|
| Under 35 | 21% |
| 35–39 | 35% |
| 40–44 | 32% |
| 45 and over | 12% |
Full details of how the survey was run are in the Methodology section at the end.
How many failed IVF cycles do patients go through?
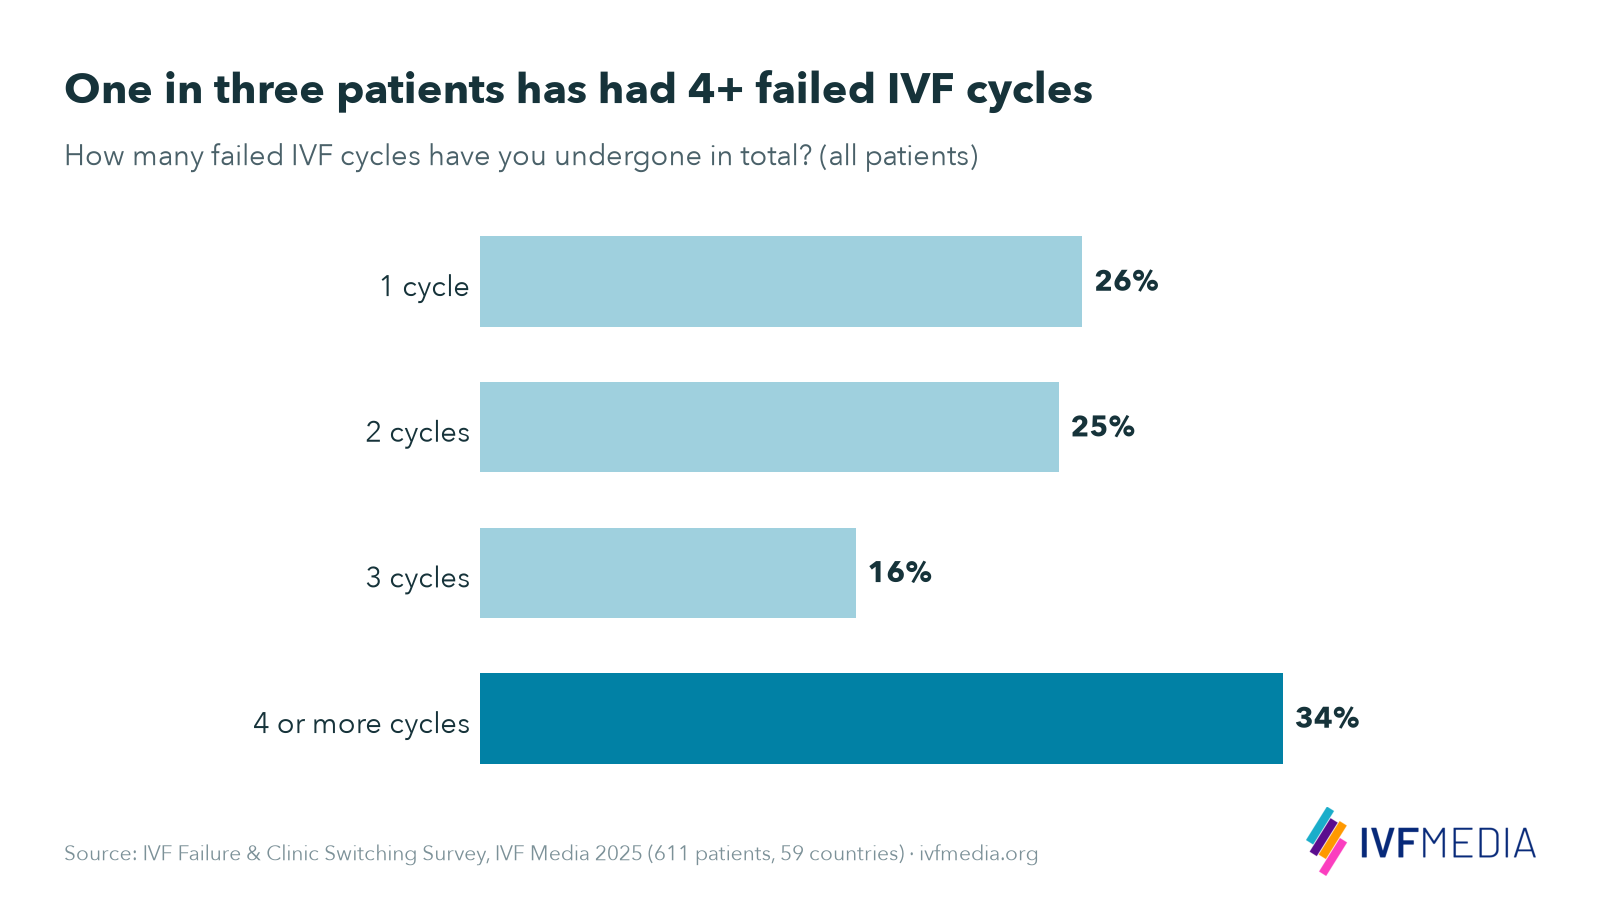
Short answer: more than most people expect. Half the patients in our survey have had three or more failed cycles, and one in three has had four or more.
| Failed IVF cycles in total | Share |
|---|---|
| 1 cycle | 25.5% |
| 2 cycles | 24.5% |
| 3 cycles | 15.9% |
| 4 or more cycles | 34.0% |
“4 or more” was the single most common answer. That’s worth sitting with for a moment. The typical patient in this survey is not someone who tried once and got unlucky. It’s someone in their late thirties, several attempts in, still trying.
Failed cycles rise with age
Age is the biggest factor in IVF success, and our data shows it clearly:
| Age group | Share with 4+ failed cycles |
|---|---|
| Under 35 | 19% |
| 35–39 | 32% |
| 40–44 | 40% |
| 45 and over | 51% |
Among patients aged 45+, more than half have been through four or more failed cycles.
Country differences
Patients in Germany (48%), Australia (44%) and Ireland (42%) were the most likely to report four or more failed cycles. Patients in Canada (29%) and the US (31%) were the least likely. Small samples in Germany and Australia mean those figures are indicative – but the pattern fits: German respondents were also the oldest group in the survey (median age 41).
Why repeated failure is so common
IVF works one embryo at a time, and most embryos don’t make it. On average, more than half of all IVF cycles fail.
The main reason is the embryo itself. Specialists estimate that around 80% of failed transfers come down to the embryo and around 20% to the uterus. And embryo quality is driven by age:
- Under 35, roughly half to 70% of embryos are chromosomally normal.
- Around 40, that falls to about one in five.
- Over 43, it’s under one in ten.
- At 44 and over, the vast majority of eggs are chromosomally abnormal.
That’s why the number of transfers it takes rises so sharply with age. A rough guide from fertility specialists:
| Age | Typical chance per transfer (own eggs) | Transfers often needed |
|---|---|---|
| Early 30s | 40–50% | 2–3 |
| 35–37 | 35–40% | 2–3 |
| Around 40 | About 20% | 3–5 |
| Over 40 | Lower still | 5–6 |
The good news is that chances add up. Large studies of hundreds of thousands of IVF cycles show cumulative live birth rates of around 30% after one complete cycle, about 45% after two, about 54% after three, and around two in three after six (all ages combined). For younger patients, cumulative success can reach 70–90%, and nearly three in four patients who keep going eventually succeed. Women aged 40–41 have around a 50% cumulative chance of a live birth after three full stimulation cycles. For success rates broken down by age, country and egg source, see Fertility Road’s guide to IVF success rates by age, country and donor eggs.
But two warnings come with that. First, most patients who succeed do so within about three transfers. After that, a good clinic should step back and reassess – not simply repeat. Second, changing clinic doesn’t reset your age. Between 40 and 43, success tends to plateau after around three cycles in total, however many clinics they’re spread across.
Many patients also stop before they’ve had a fair chance. Emotional exhaustion – not money, not medical advice – is the number one reason patients stop treatment before getting pregnant.
What this means for you: if your first cycle failed, you are in the majority, not the exception. One failed cycle tells you something – but rarely everything. The question that matters is what you learn from it.
Were patients told that IVF might fail?
One in four patients (26%) says their doctor did not explain the potential outcomes of IVF – including the risk of failure – before treatment started. Three in four (74%) say they were informed.
That’s 157 people out of 611 who went into one of the most expensive and emotional medical journeys of their lives without a clear picture of the odds.
| Country of residence | Informed about risk of failure |
|---|---|
| Ireland | 80% |
| United Kingdom | 78% |
| United States | 76% |
| Germany | 72% |
| Other countries | 70% |
| Canada | 69% |
| Australia | 66% |
Even in the best-performing countries, one in five patients says they weren’t told.
Why it matters: uninformed patients are more likely to leave
This isn’t just a box-ticking issue. Patients who weren’t warned about the risk of failure were more likely to change clinic later – 46% switched, compared with 39% of informed patients.
And when uninformed patients did switch, poor communication was a much bigger reason: 46% of them cited it, compared with 34% of switchers who had been informed.
The lesson is simple. Honest expectations at the start protect the patient-clinic relationship when things go wrong. Patients can cope with bad odds. What they struggle to forgive is feeling misled.
What this means for you: before any cycle, ask your doctor directly – “What is my realistic chance of a live birth from this cycle, given my age and test results?” Ask for a number, not a reassurance. A good clinic will give you one.
How many patients change IVF clinic after a failed cycle?
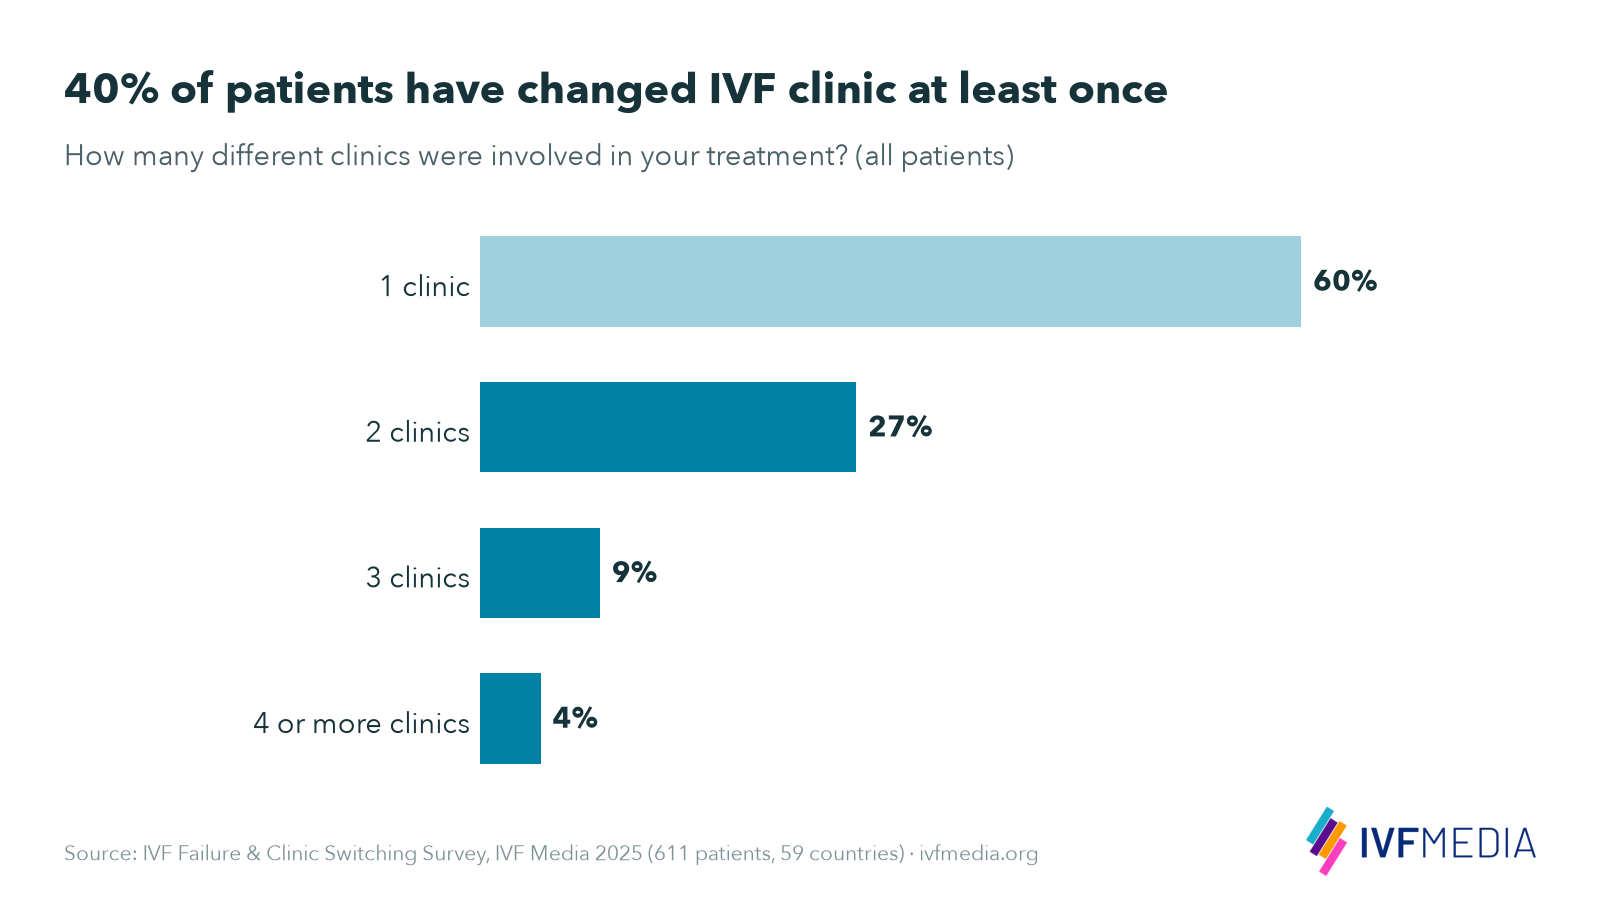
40% of patients in our survey have changed IVF clinic at least once. 247 out of 611 have been treated at two or more clinics.
| Clinics involved in treatment | Share |
|---|---|
| 1 clinic | 59.6% |
| 2 clinics | 27.3% |
| 3 clinics | 8.7% |
| 4 or more clinics | 4.4% |
One in eight patients (13%) has been through three clinics or more.
Switching snowballs with every failed cycle
The more cycles fail, the more likely patients are to move on. By the fourth failed cycle, staying with one clinic becomes the minority choice.
| Failed cycles | Share who have used 2+ clinics |
|---|---|
| 1 cycle | 14% |
| 2 cycles | 25% |
| 3 cycles | 46% |
| 4 or more cycles | 69% |
Among patients with four or more failed cycles, nearly one in three (30%) has been through three or more clinics.
Older patients switch more
| Age group | Share who have switched clinic |
|---|---|
| Under 35 | 29% |
| 35–39 | 38% |
| 40–44 | 43% |
| 45 and over | 60% |
Switching by country
| Country of residence | Share who have switched clinic |
|---|---|
| Canada | 49% |
| Ireland | 48% |
| Germany* | 40% |
| United Kingdom | 37% |
| United States | 34% |
| Australia* | 31% |
| Other countries | 53% |
*Small sample – indicative only.
Patients outside the six largest markets were the most mobile (53%). Many of them had already crossed borders for treatment – which, by definition, means changing clinic.
When do patients decide to leave their IVF clinic?
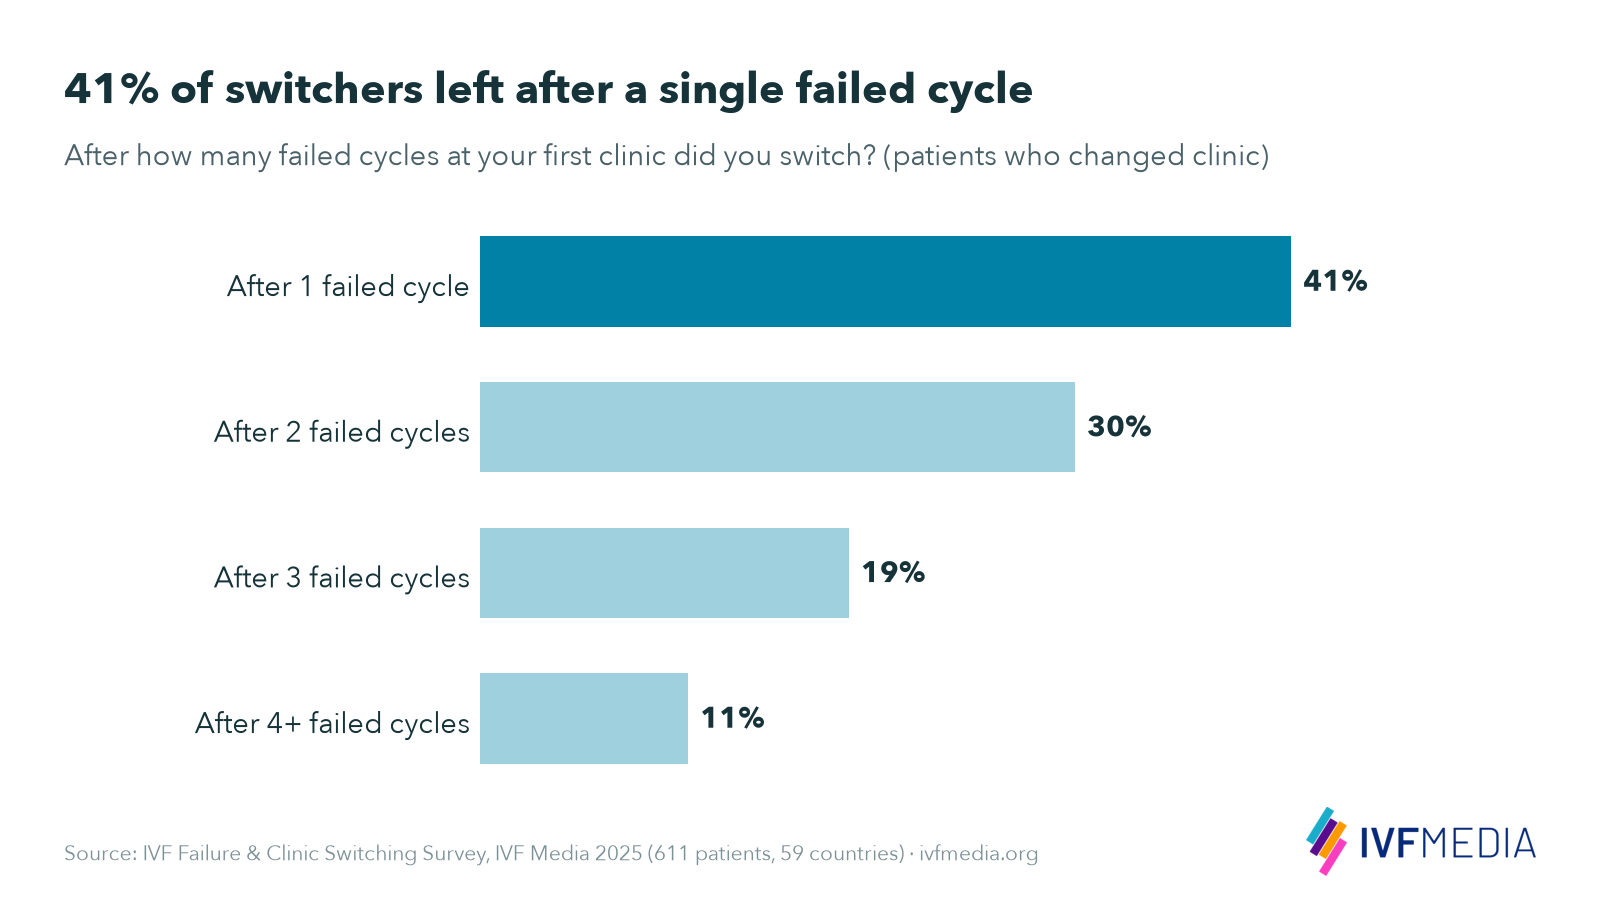
Fast. 41% of patients who changed clinic did so after just one failed cycle. 71% left within two failed cycles.
| Switched after… | Share of switchers |
|---|---|
| 1 failed cycle | 40.9% |
| 2 failed cycles | 30.0% |
| 3 failed cycles | 18.6% |
| 4 or more failed cycles | 10.5% |
Published data on how often IVF patients change clinic is surprisingly scarce. This survey is one of the few to measure it directly – and the answer is: early, and often.
For clinics, this is a stark number. The first failed cycle is the make-or-break moment for the relationship. What happens in the weeks after a negative test – the follow-up call, the review consultation, the plan for next time – decides whether a patient stays.
Why do patients change IVF clinic?
The most common reason is a disappointing result (57%). But how the clinic behaves matters almost as much: 51% of switchers cited poor communication, a poor relationship with their doctor, or both.
Patients could choose more than one reason, so the shares add up to more than 100%.
| Reason for changing clinic | Share of switchers |
|---|---|
| Disappointing outcome of previous treatment | 57% |
| Poor communication with the clinic during treatment | 38% |
| Relationship with the leading doctor | 36% |
| Cost was higher than expected | 11% |
| The clinic’s promise was not delivered | 9% |
| Other reason (written in) | 26% |
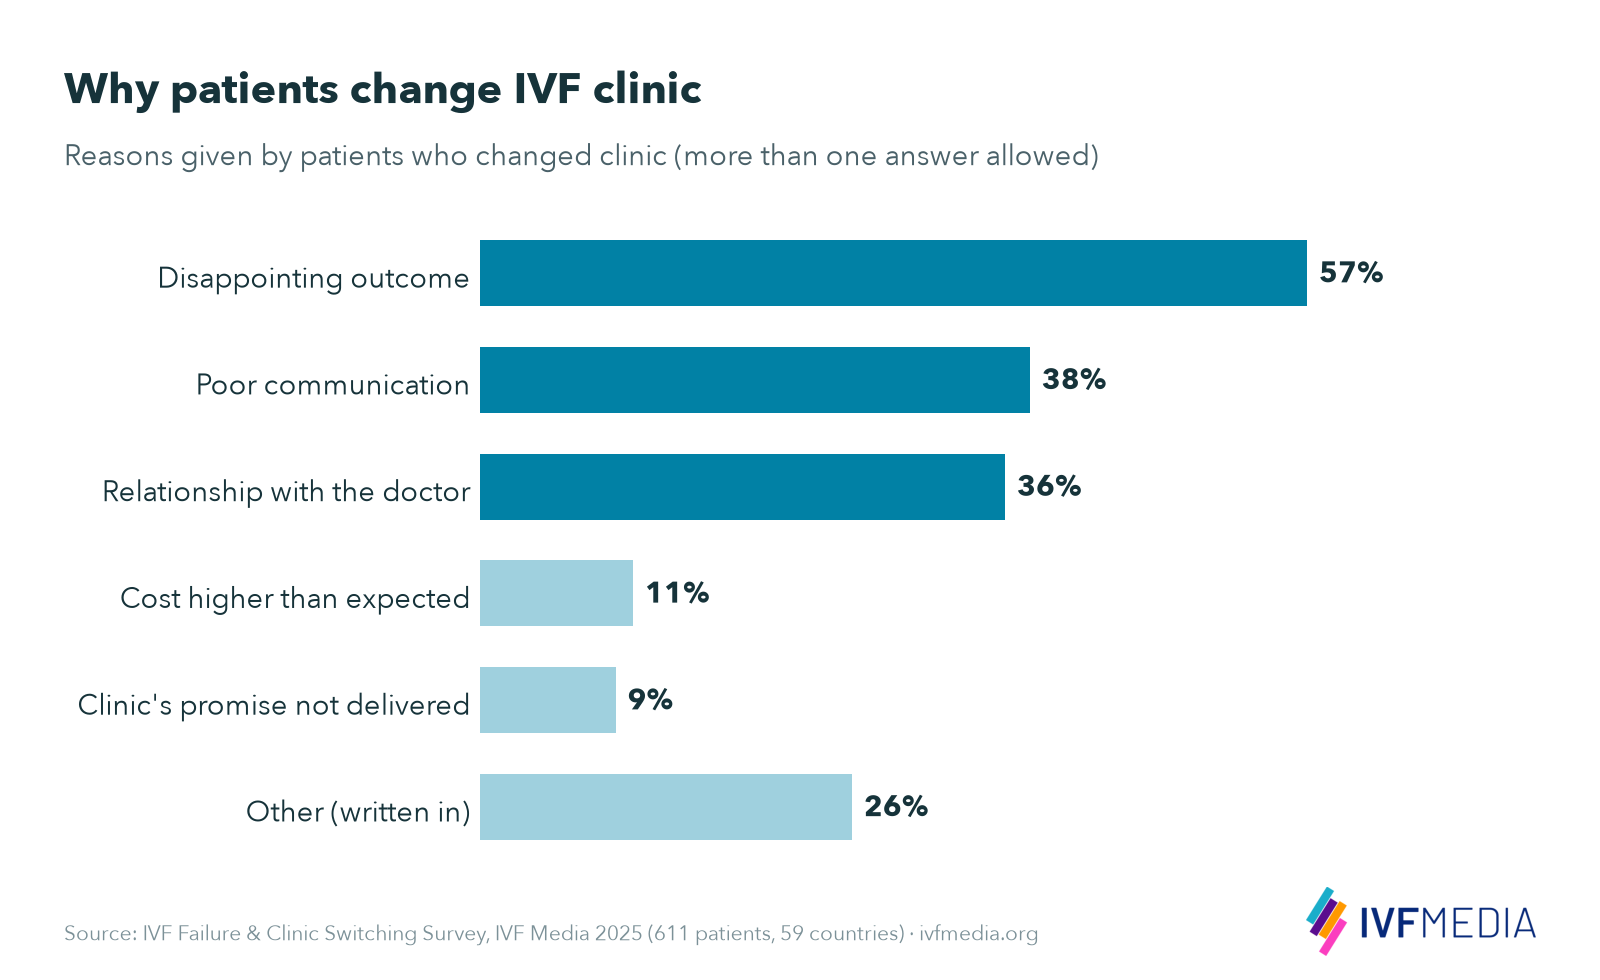
Two numbers stand out.
First, cost barely registers. Only 11% of switchers left because treatment cost more than expected. Patients will pay a lot. What they won’t accept is paying a lot and feeling unheard.
Second, one in five switchers (21%) left for care-related reasons without even mentioning the outcome. Their cycle failed – but that’s not what they blamed. They blamed the communication, or the doctor.
What patients wrote in their own words
63 patients wrote their own reasons. We grouped them into themes:
| Theme | Share of written-in reasons |
|---|---|
| Same protocol repeated, no new tests, care not personalised | 27% |
| Public funding or insurance ran out or changed | 24% |
| Location, relocation or travel | 14% |
| Clinic age limit, or pushed towards donor eggs | 13% |
| Clinic refused or discouraged further treatment | 10% |
| Wanted a second opinion or real answers | 10% |
| Lack of empathy, trust or a cold atmosphere | 8% |
| Clinic closed, was sold, lab shut, or doctor moved | 6% |
Some answers covered more than one theme, so shares add up to more than 100%.
The biggest single theme is a clinic that kept doing the same thing. Patients described doctors who “insisted on using the same protocol”, clinics “doing the same plan over and over”, and teams that “did not offer” tests like endometrial receptivity analysis. One patient summed it up: they didn’t feel the clinic was doing “anything more than the standard treatment even though it clearly wasn’t working.”
Others described feeling “just a number”, with “no aftercare” after a negative result. One wrote that “vital info was withheld”. Another moved clinics after three failed cycles with “no data or answers” – and got answers at the next clinic after one cycle.
Age limits also pushed patients out. Several were told they could no longer use their own eggs past 42 or 43. Some weren’t ready to accept donor eggs and went looking for a clinic that would try again with their own.
Early leavers blame communication. Late leavers blame results.
This is one of the most revealing patterns in the data. The reasons for leaving change depending on when patients leave:
| Switched after… | Outcome | Communication | Doctor relationship | Cost |
|---|---|---|---|---|
| 1 failed cycle | 47% | 42% | 37% | 12% |
| 2 failed cycles | 62% | 42% | 43% | 15% |
| 3 failed cycles | 65% | 35% | 33% | 2% |
| 4+ failed cycles | 65% | 15% | 19% | 8% |
Patients who leave after one cycle are almost as likely to blame communication (42%) as the result (47%). Patients who stay for four or more cycles before leaving rarely complain about communication (15%) – they leave because the results never came.
In other words: a clinic that communicates well buys itself time. A clinic that communicates badly loses patients before it has a fair chance to succeed.
Reasons for switching clinic, by country
| Country | Outcome | Communication | Doctor | Cost | Promise not delivered |
|---|---|---|---|---|---|
| United States | 65% | 42% | 42% | 14% | 10% |
| United Kingdom | 48% | 45% | 38% | 12% | 10% |
| Ireland | 42% | 16% | 32% | 11% | 5% |
| Canada | 35% | 24% | 24% | 6% | 0% |
| Australia* | 60% | 50% | 50% | 0% | 0% |
| Germany* | 60% | 60% | 40% | 0% | 30% |
| Other countries | 61% | 32% | 29% | 10% | 10% |
*Very small samples – indicative only.
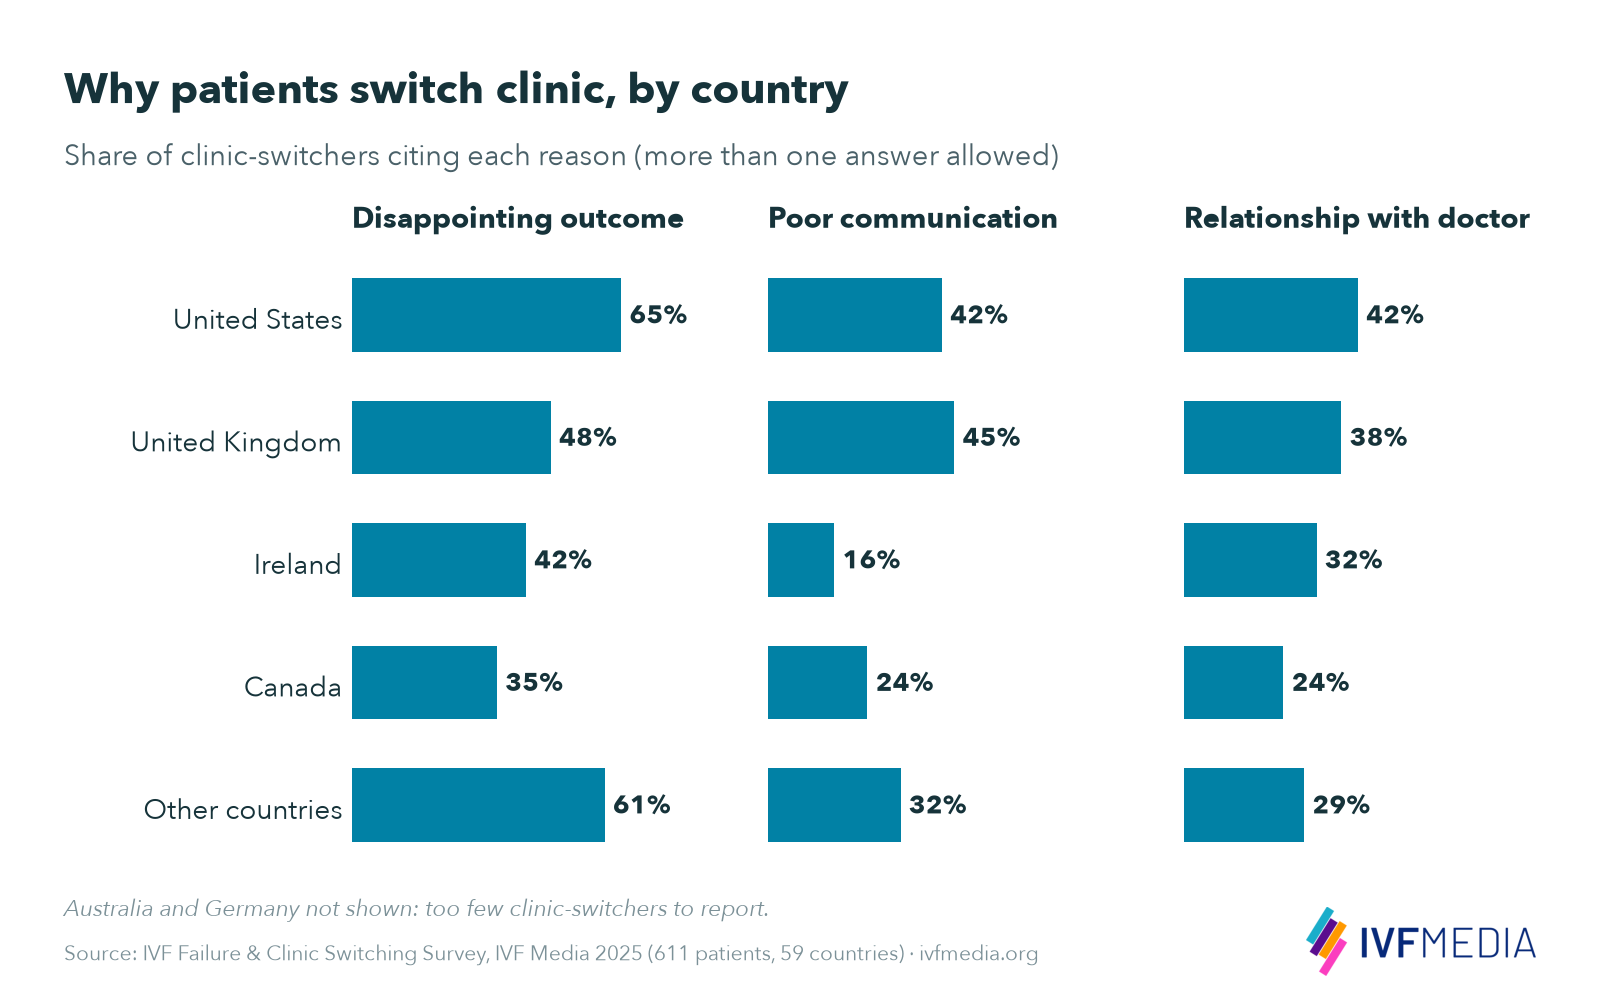
What the country data shows:
- US patients are the most demanding on results. 65% of US switchers cited a disappointing outcome – the highest of any large group. US patients also had the highest cost complaint (14%), which fits with the highest out-of-pocket spending in the survey (see below).
- UK patients are the most frustrated with communication. 45% of UK switchers cited poor communication – almost as many as cited the outcome (48%). UK switchers were also the most likely to write in their own reason (48%). Their most common written answer? Public funding running out. Many UK patients get one or two funded cycles, then move to a private clinic – or abroad – when funding stops.
- Irish and Canadian patients switch for other reasons. Only 16% of Irish switchers and 24% of Canadian switchers cited communication. Nearly half of Canadian switchers (47%) wrote their own reason – often relocation, insurance changes or access to a provincial funding programme.
- In Germany, broken promises stand out. 3 in 10 German switchers said the clinic’s promise wasn’t delivered – by far the highest rate. The sample is small, but the signal is worth watching.
How much have patients spent on IVF out of pocket?
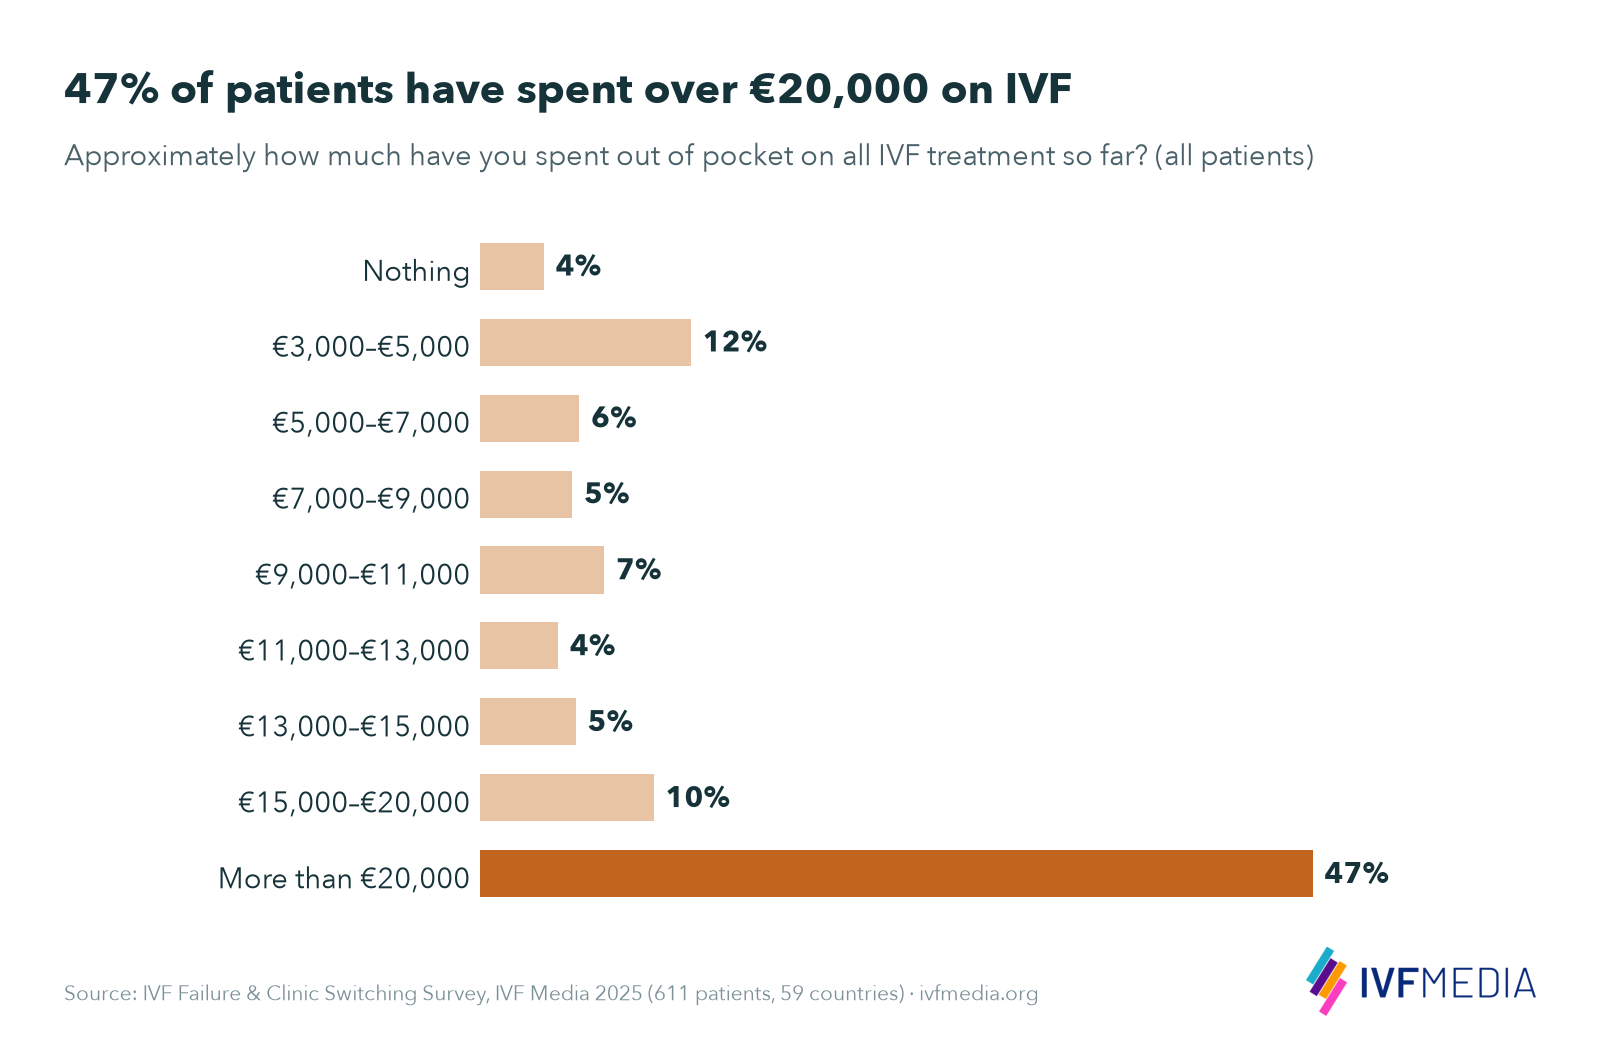
47% of patients have spent more than €20,000 of their own money on IVF. Nearly six in ten (57%) have spent more than €15,000. Only 4% have spent nothing.
| Out-of-pocket spend so far | Share |
|---|---|
| Nothing | 3.6% |
| €3,000–€5,000 | 11.9% |
| €5,000–€7,000 | 5.6% |
| €7,000–€9,000 | 5.2% |
| €9,000–€11,000 | 7.0% |
| €11,000–€13,000 | 4.4% |
| €13,000–€15,000 | 5.4% |
| €15,000–€20,000 | 9.8% |
| More than €20,000 | 47.0% |
“More than €20,000” is the most common answer by a wide margin – nearly five times more common than any other bracket.
Out-of-pocket IVF spending by country
This is where the differences become dramatic.
| Country of residence | €0 | €3k–€9k | €9k–€15k | €15k–€20k | More than €20k | Typical (median) spend |
|---|---|---|---|---|---|---|
| United States | 0% | 21% | 13% | 7% | 59% | Over €20,000 |
| Australia* | 0% | 19% | 19% | 6% | 56% | Over €20,000 |
| Canada | 0% | 23% | 9% | 14% | 54% | Over €20,000 |
| Ireland | 8% | 10% | 20% | 10% | 52% | Over €20,000 |
| Germany* | 4% | 8% | 36% | 8% | 44% | €15,000–€20,000 |
| United Kingdom | 9% | 24% | 20% | 16% | 31% | €13,000–€15,000 |
| Other countries | 5% | 33% | 18% | 9% | 34% | €13,000–€15,000 |
*Small sample – indicative only.
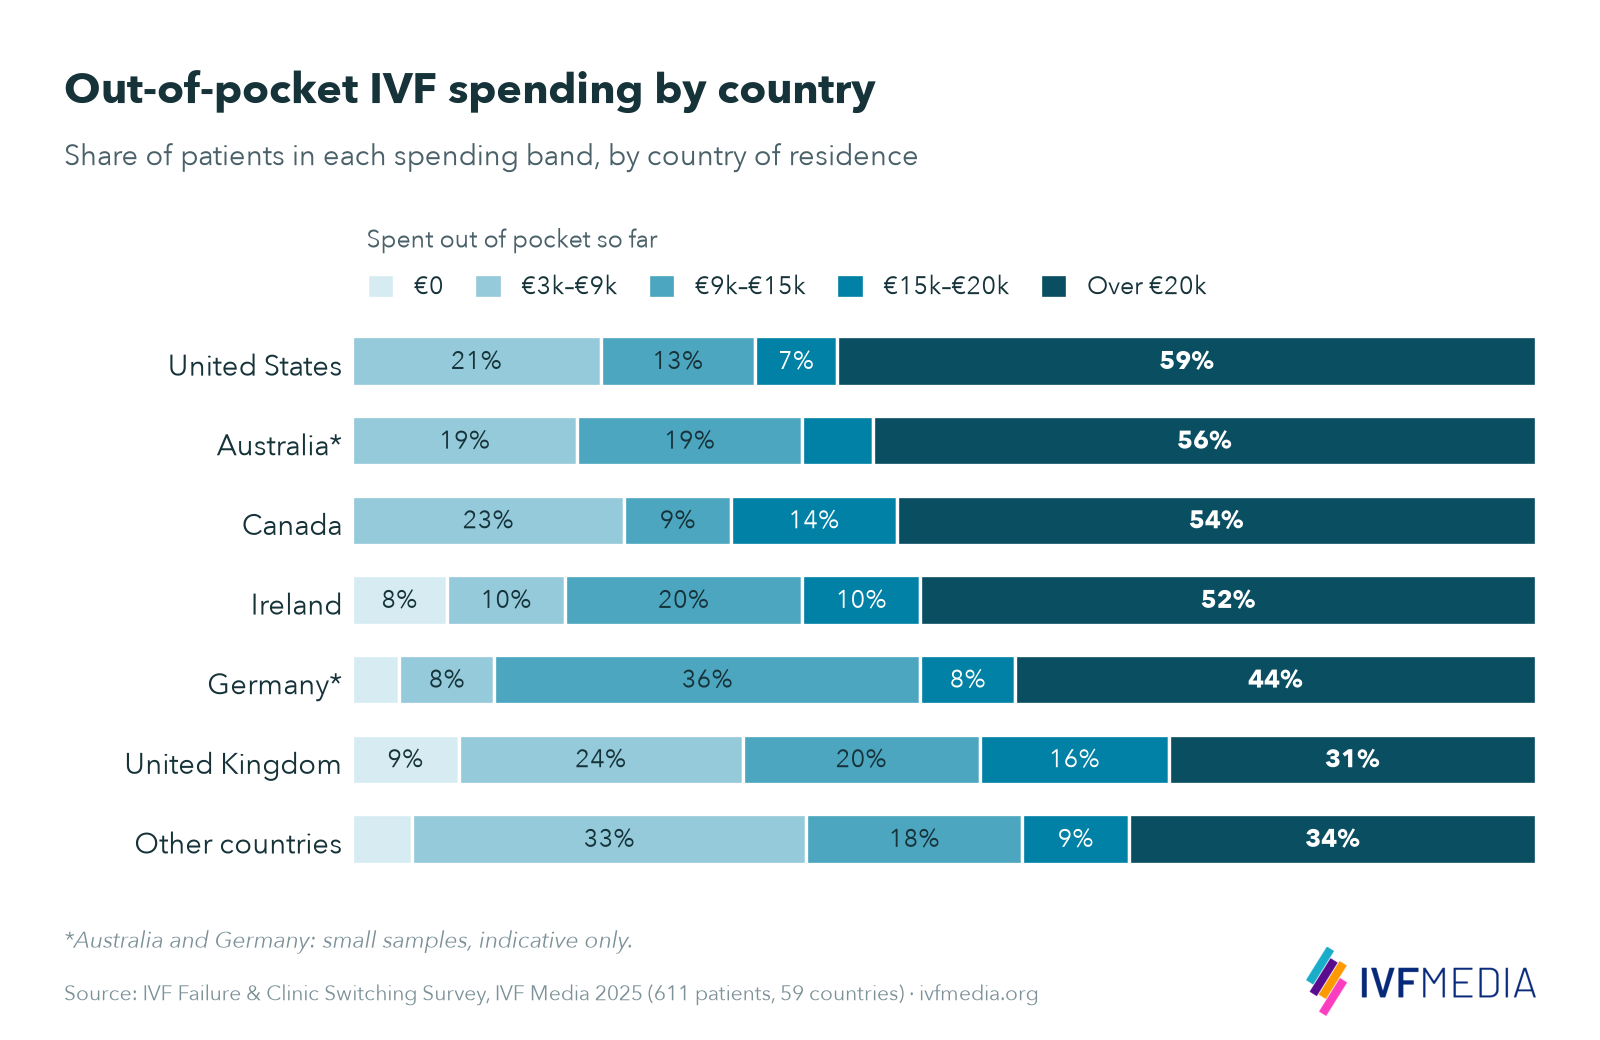
In four of the six largest markets – the US, Australia, Canada and Ireland – the typical patient has already spent more than €20,000. Not a few patients. More than half.
Who pays for IVF? Financing by country
How patients pay explains much of the spending gap:
| Country | Completely self-funded | Insurance + self-pay | Partly public-funded | Fully public-funded |
|---|---|---|---|---|
| All patients | 51% | 28% | 15% | 6% |
| United States | 38% | 59% | 1% | 2% |
| United Kingdom | 61% | 2% | 24% | 13% |
| Ireland | 72% | 10% | 8% | 10% |
| Canada | 51% | 26% | 23% | 0% |
| Australia* | 34% | 6% | 59% | 0% |
| Germany* | 68% | 16% | 16% | 0% |
*Small sample – indicative only.
Here’s what stands out, country by country:
- United States: insurance doesn’t protect patients from huge bills. 59% of US patients combine insurance with self-pay – yet 59% have still spent over €20,000. Among fully self-funded US patients, the figure is 81%. Even a single failed cycle is expensive: 32% of US patients with just one failed cycle have already spent over €20,000, compared with 11% of one-cycle patients elsewhere. Among US patients with four or more failed cycles, 79% are past €20,000.
- United Kingdom: public funding softens the blow – for some. 37% of UK patients had at least some public funding, and 9% have spent nothing at all. That’s why the UK has the lowest out-of-pocket spending of the big markets. But 61% are fully self-funded, and 31% have still spent over €20,000.
- Ireland: the most self-funded market. 72% of Irish patients paid for everything themselves – the highest of any country. Over half (52%) have spent more than €20,000.
- Canada: a patchwork. Around a quarter of Canadian patients had partial public funding, a quarter combined insurance with self-pay, and half paid everything themselves. 54% have spent over €20,000.
- Australia: public rebates, still high costs. 59% of Australian patients had partial public funding – the highest of any country – yet 56% have still spent over €20,000.
- Germany: partial cover, mostly self-funded. 68% of German patients self-funded completely. German spending clusters in the middle: 36% spent €9,000–€15,000.
Why IVF costs so much at home: price and funding by country
The survey shows what patients actually paid. Here’s the context behind those numbers – typical prices and public funding rules in each country (as of 2026):
| Country | Typical cost of one own-egg IVF cycle | Public funding |
|---|---|---|
| United States | $15,000–$20,000 base; $20,000–$25,000+ all-in (about €17,500–€22,000) | No national cover. About 15 states have IVF insurance mandates. Employer cover is growing but patchy. |
| Canada | C$12,000–C$16,000; up to about C$22,000 all-in (about €11,000–€14,000) | Varies by province. Ontario and Quebec fund one cycle; British Columbia introduced one funded cycle in 2025. |
| Ireland | €6,000–€7,000; up to €10,000 with extras | Public scheme since September 2023: one funded cycle for eligible couples (woman 40 or under, own eggs and sperm only). |
| United Kingdom | £5,000–£10,000 (about €5,800–€11,600) | Guidelines recommend three funded cycles under 40, but most areas of England fund only one – and some areas cut funding further in 2026. Scotland funds up to three. |
| Australia | A$10,000–A$13,500 gross; about A$4,400–A$8,800 out of pocket after rebates (about €2,500–€5,100) | Medicare rebates cover part of each cycle. |
| Germany | About €3,000–€6,000 all-in | Statutory insurance pays 50% of three cycles – but only for married couples aged 25–40 using their own eggs and sperm. |
Medication, ICSI, embryo freezing, frozen transfers and genetic testing of embryos often come on top. In the UK, the real cost of a cycle is typically around 60% higher than the advertised price once extras are included (see Fertility Road’s IVF cost guide for the UK, including NHS funding). In the US, genetic testing of embryos alone can add $3,000–$6,000.
Two things explain the survey’s results. First, prices: a single US cycle can cost what four or five cycles cost abroad. Second, eligibility: public funding in most countries runs out after one cycle, excludes older patients, or excludes donor eggs. After four failed cycles – where a third of our patients are – almost everyone is paying privately.
The more cycles fail, the more it costs
| Failed cycles | Share who have spent more than €20,000 |
|---|---|
| 1 cycle | 19% |
| 2 cycles | 40% |
| 3 cycles | 50% |
| 4 or more cycles | 72% |
Nearly three in four patients with four or more failed cycles have spent more than €20,000. Each failed cycle doesn’t just cost emotionally. It compounds financially.
Would patients consider IVF treatment abroad?
Yes – 62% of patients (376 of 611) would consider IVF treatment abroad. Only 38% would not.
By country of residence
| Country of residence | Would consider IVF abroad |
|---|---|
| Germany* | 80% |
| United Kingdom | 75% |
| Ireland | 73% |
| Other countries | 70% |
| Canada | 66% |
| United States | 48% |
| Australia* | 47% |
*Small sample – indicative only.
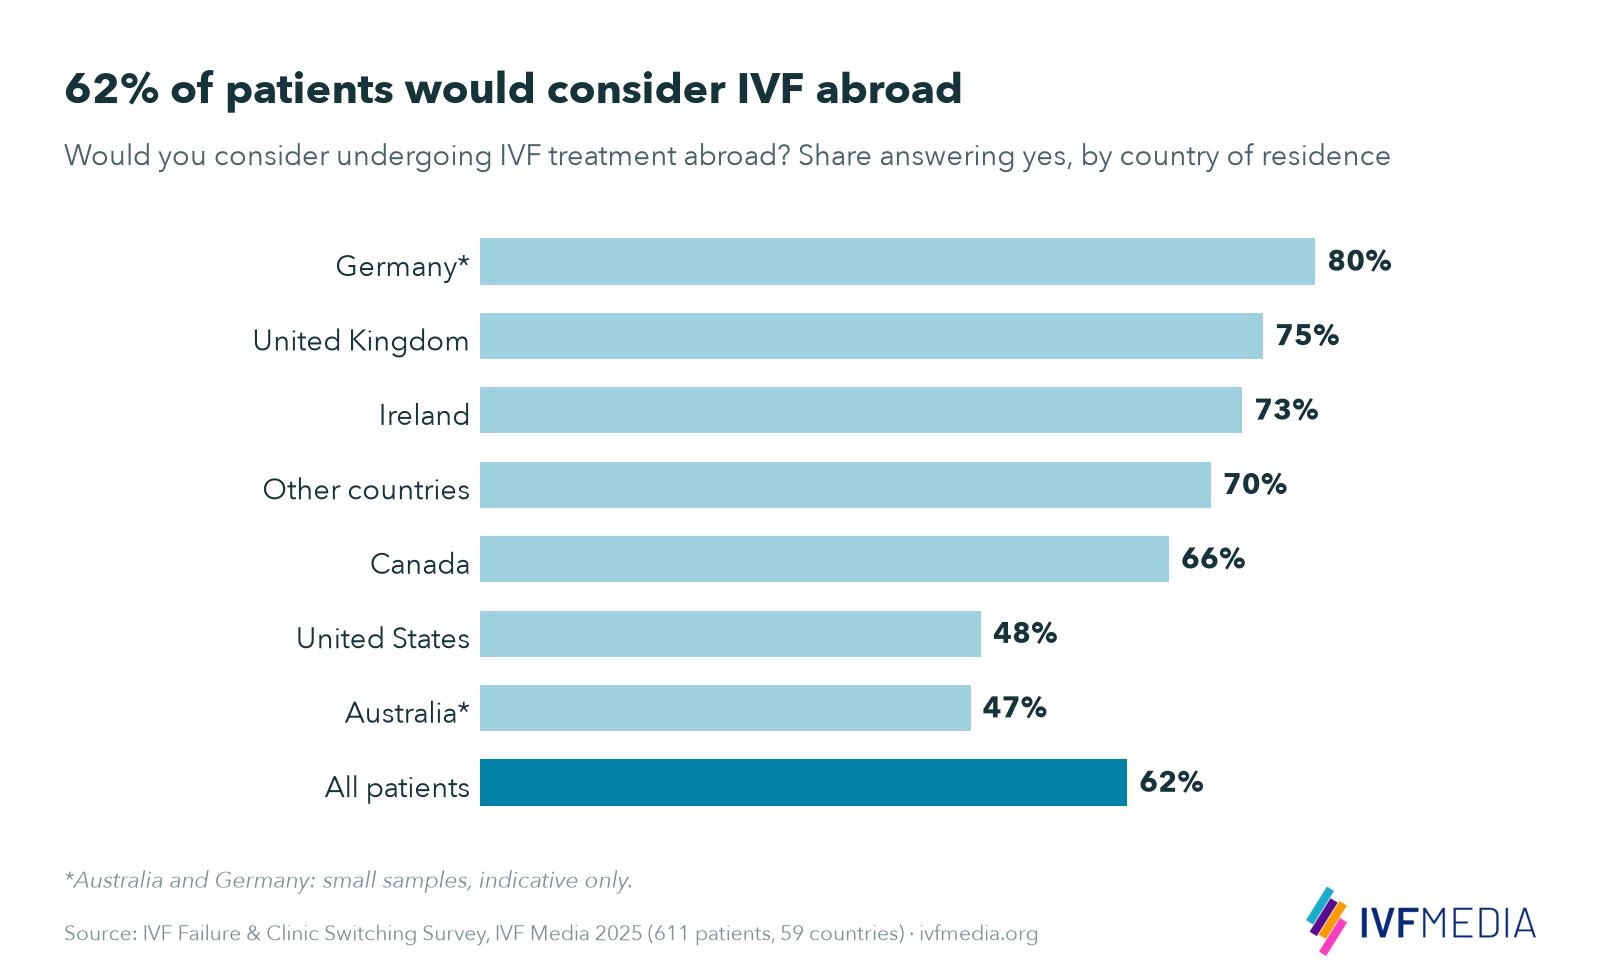
European patients are the most open. For a patient in London, Dublin or Munich, a top clinic in Spain, Greece or the Czech Republic is a short flight away. For patients in the US and Australia, the distances are bigger, and fewer have done it before.
Who is most open to going abroad?
Openness to treatment abroad rises with every sign of a difficult journey:
| Patient group | Would consider IVF abroad |
|---|---|
| Aged under 35 | 48% |
| Aged 35–39 | 60% |
| Aged 40–44 | 64% |
| Aged 45 and over | 81% |
| 1 failed cycle | 56% |
| 4+ failed cycles | 68% |
| Stayed with one clinic | 53% |
| Already switched clinic | 74% |
| Insurance + self-pay | 47% |
| Completely self-funded | 71% |
The pattern is clear. Older patients, patients with more failed cycles, patients who’ve already switched clinic and patients paying their own way are the most open to treatment abroad.
The age effect is especially strong. Four in five patients aged 45+ would consider going abroad. Part of the reason is simple: many clinics at home stop treating patients at a certain age, while several popular destinations treat patients for longer. Typical legal age limits for treatment are around 50 in Spain and Portugal, 48–49 in the Czech Republic, 54 in Greece and up to 58 in Northern Cyprus (see the full IVF age-limit guide by country). For older patients, donor-egg treatment abroad is often the most realistic route – with success rates per transfer of roughly 55–65% regardless of the recipient’s age.
The funding effect matters too. In the UK, 84% of fully self-funded patients would consider going abroad, compared with 62% of patients who’ve had some NHS funding. Once patients are paying privately anyway, the price gap between home and abroad becomes impossible to ignore.
One in five has already been abroad
20% of patients (123 of 611) had their most recent IVF cycle in a country other than where they live.
The most common destinations were:
| Destination of last IVF cycle | Share of patients treated abroad |
|---|---|
| Greece | 20% |
| Spain | 18% |
| Czech Republic | 17% |
| Cyprus | 6% |
| Mexico | 5% |
| Ireland | 5% |
| Portugal | 4% |
Greece, Spain and the Czech Republic are also the most popular destinations patients shortlist when they research treatment abroad.
Cross-border treatment was most common among patients from the UK (36% had their last cycle abroad), Ireland (32%) and Germany (32%). It was rare among patients from Canada (14%), the US (6%) and Australia (3%). US patients who did travel most often went to Mexico or the Czech Republic.
These patients tend to have harder histories: 50% have had four or more failed cycles (compared with 30% of patients treated at home), and 65% have changed clinic at least once (compared with 34%).
The most striking number: 96% of patients who had their last cycle abroad would consider treatment abroad again. Among patients treated at home, it’s 53%. Going abroad, it seems, rarely puts patients off going abroad.
How much would patients spend on IVF abroad?
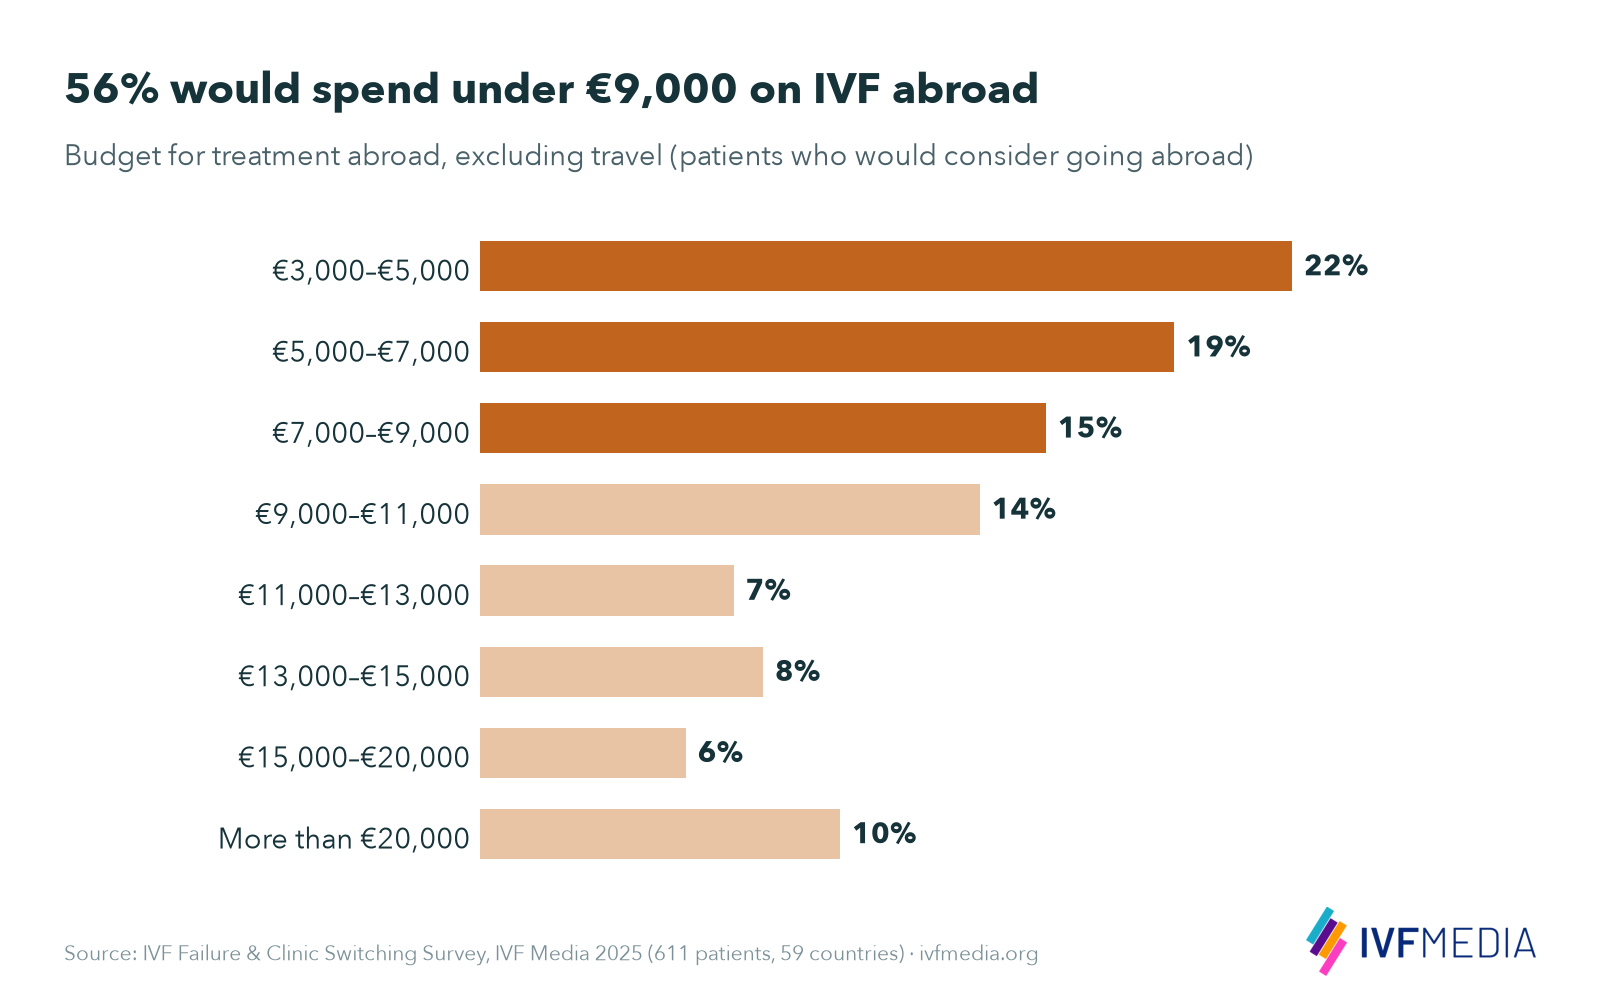
56% of patients open to treatment abroad have a budget under €9,000. The most common budget is €3,000–€5,000 (22%). These figures cover treatment only – not flights or accommodation.
| Budget for IVF abroad (treatment only) | Share |
|---|---|
| €3,000–€5,000 | 22.1% |
| €5,000–€7,000 | 18.9% |
| €7,000–€9,000 | 15.4% |
| €9,000–€11,000 | 13.6% |
| €11,000–€13,000 | 6.9% |
| €13,000–€15,000 | 7.7% |
| €15,000–€20,000 | 5.6% |
| More than €20,000 | 9.8% |
Budget for IVF abroad by country
| Country of residence (patients open to going abroad) | €3k–€7k | €7k–€11k | €11k–€20k | More than €20k | Median budget |
|---|---|---|---|---|---|
| Germany* | 25% | 30% | 25% | 20% | €9,000–€11,000 |
| Canada | 26% | 39% | 22% | 13% | €9,000–€11,000 |
| United States | 32% | 33% | 25% | 11% | €9,000–€11,000 |
| United Kingdom | 45% | 29% | 20% | 6% | €7,000–€9,000 |
| Ireland | 52% | 21% | 14% | 14% | €5,000–€7,000 |
| Australia* | 60% | 13% | 27% | 0% | €5,000–€7,000 |
| Other countries | 49% | 26% | 14% | 10% | €7,000–€9,000 |
*Small sample – indicative only.
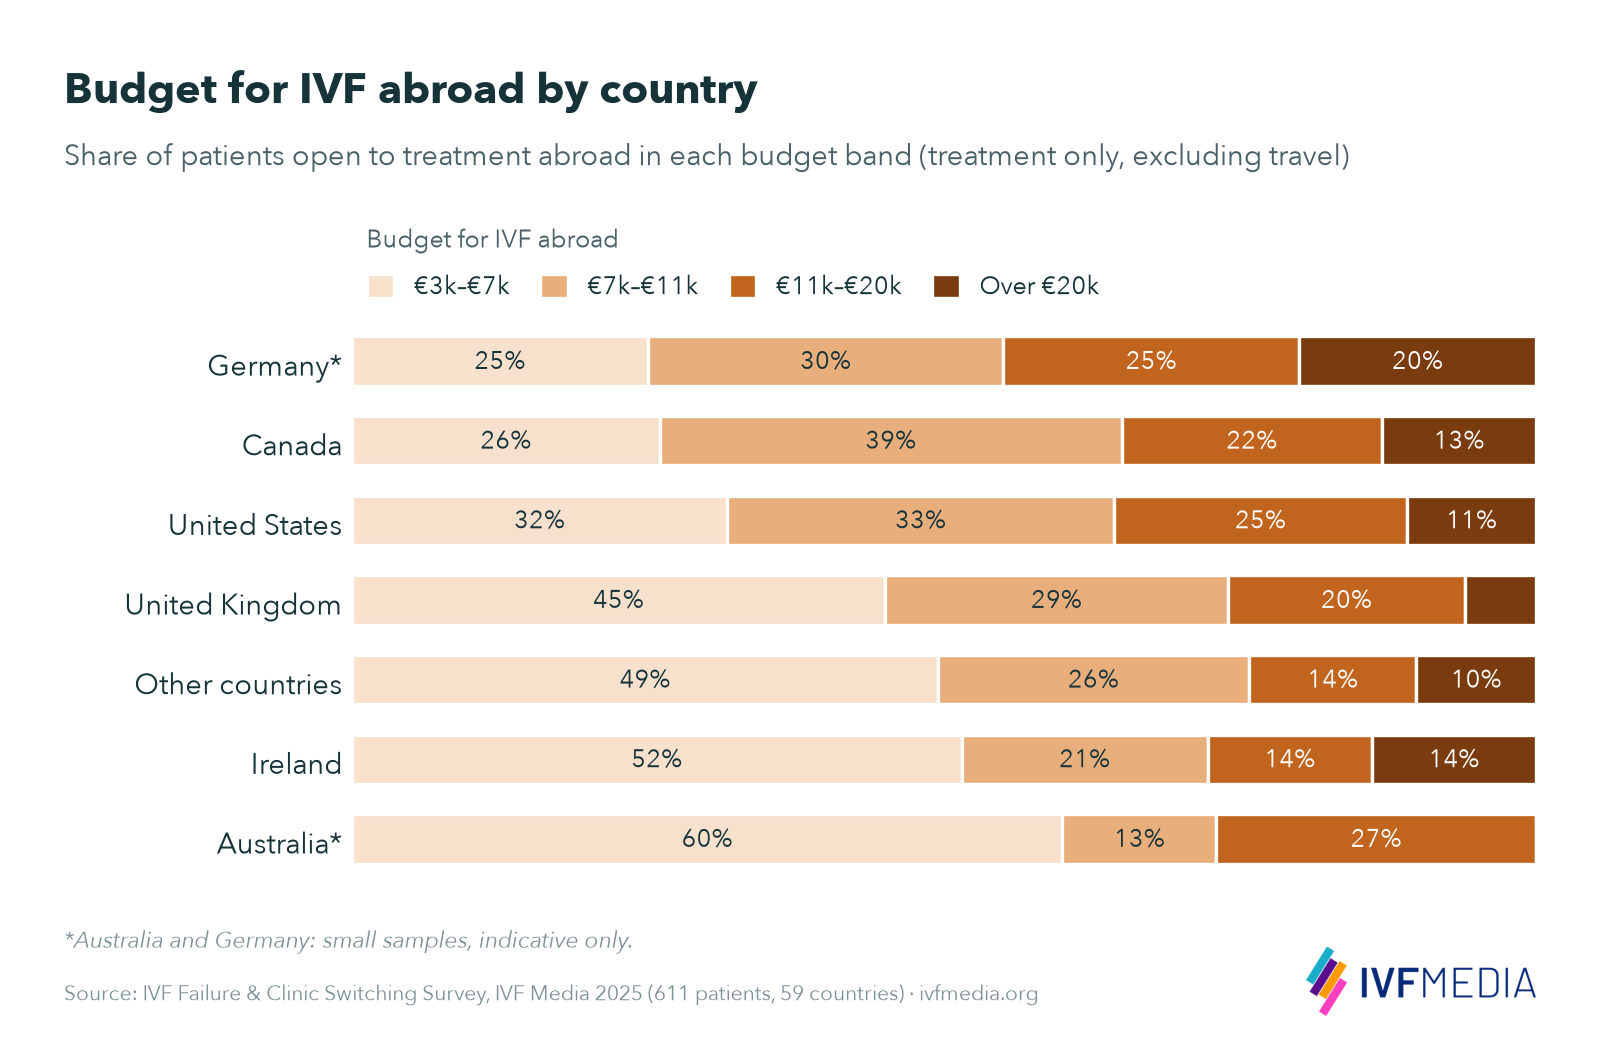
What the country budgets tell us:
- German, Canadian and US patients plan the biggest budgets. Their median budget is €9,000–€11,000. One in five German patients (20%) would spend more than €20,000 abroad.
- UK patients sit in the middle, with a median budget of €7,000–€9,000. Only 6% would go above €20,000.
- Irish and Australian patients plan the tightest budgets. More than half (52% and 60%) budget €3,000–€7,000. For Irish patients, this is striking: they’re among the highest spenders at home, yet most plan a modest budget abroad. (For comparison, see how much patients budget for IVF abroad in our earlier survey.)
The budget paradox
Put the two sets of numbers side by side and something jumps out.
287 patients have already spent more than €20,000 on IVF at home. 185 of them (64%) would consider going abroad. Yet nearly half of those big spenders (46%) budget under €9,000 for treatment abroad.
Patients aren’t going abroad to spend more. They’re going abroad because they can’t keep spending what they’ve spent. Treatment abroad is how they make one more attempt affordable.
What does a typical budget buy abroad?
Here’s how patients’ budgets compare with typical base-package prices at popular European destinations:
| Destination | IVF with own eggs | IVF with donor eggs | Embryo donation |
|---|---|---|---|
| Czech Republic | €2,500–€3,500 | €5,500–€7,000 | €2,200–€3,500 |
| Greece | €2,500–€3,500 | €5,500–€7,000 | €3,500–€6,000 |
| Northern Cyprus | €2,500–€3,000 | €5,500–€7,000 | – |
| Portugal | €4,000–€4,600 | €6,500–€7,500 | €2,000–€2,400 |
| Spain | €3,600–€6,700 | €6,500–€8,500 | €3,000–€5,000 |
Typical base-package prices, 2026. Prices vary by clinic.
So a €3,000–€5,000 budget – the most common answer – can cover own-egg IVF in the Czech Republic, Greece or Northern Cyprus. Donor-egg treatment usually needs €5,500 or more. Compare prices country by country in FertilityClinicsAbroad’s guide to the cheapest IVF in Europe and what the price includes.
But base packages are just the start. Medication (often €1,000–€3,000), frozen embryo transfers, embryo freezing and storage, genetic testing and initial tests usually cost extra. A realistic total is typically €1,500–€3,500 above the advertised price. A simple rule of thumb: add around 30% to any headline price.
For patients with several failed cycles, multi-cycle refund programmes are worth knowing about. Three-cycle packages with a refund if treatment doesn’t succeed typically cost around €16,000–€18,000 in Spain, Greece, the Czech Republic, Cyprus and Portugal. Own-egg refund programmes usually have an age cap of around 39–40; donor-egg programmes accept patients up to around 50–55.
What stops patients from going abroad for IVF?
Travel costs and logistics are by far the biggest barrier, named by 76% of patients who wouldn’t consider treatment abroad. Concerns about treatment cost come last, at 20%.
| Reason for not considering IVF abroad | Share (of 235) |
|---|---|
| Travel costs and logistics | 76% |
| Concerns about quality of care or IVF regulations | 36% |
| Language barrier or cultural differences | 34% |
| Already satisfied with local treatment or clinics | 32% |
| Cost of treatment | 20% |
| Other reason (written in) | 10% |
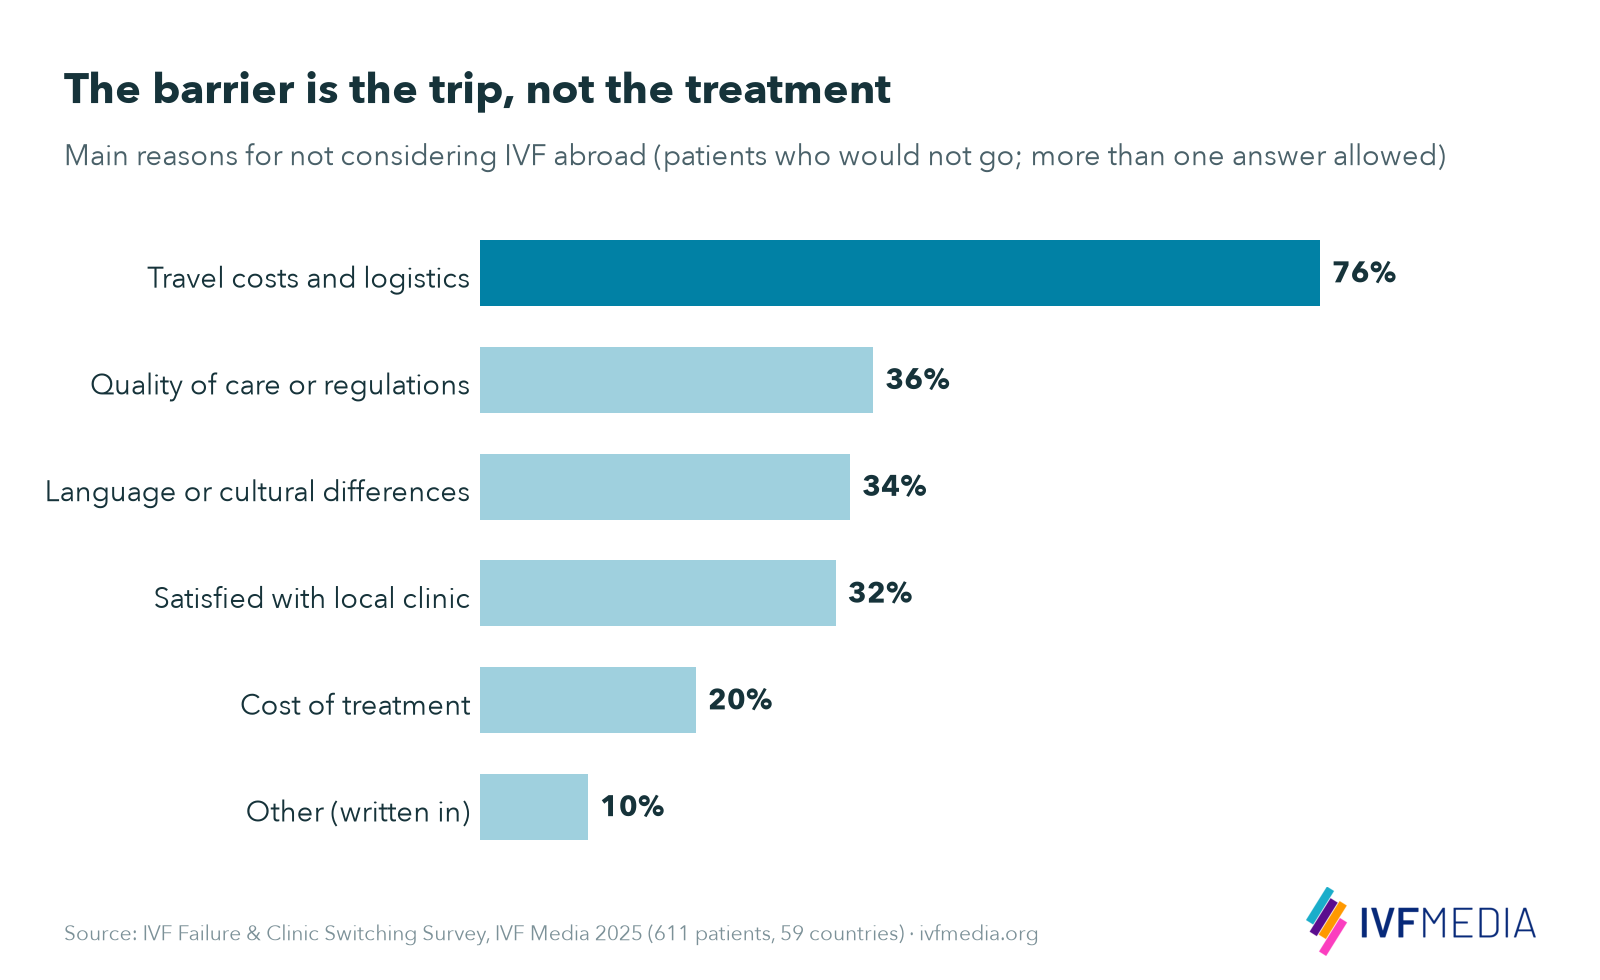
The barrier is the trip, not the treatment. Nearly four times as many patients worry about getting there as about what the treatment costs.
Barriers by country
| Country (patients not considering abroad) | Travel & logistics | Quality / regulation | Language & culture | Satisfied locally | Treatment cost |
|---|---|---|---|---|---|
| United States | 81% | 40% | 37% | 32% | 20% |
| United Kingdom | 79% | 57% | 54% | 32% | 0% |
| Australia* | 76% | 53% | 29% | 35% | 18% |
| Other countries | 67% | 18% | 23% | 33% | 41% |
*Small sample – indicative only. Ireland, Canada and Germany had too few patients answering this question to report separately.
- US patients worry about logistics above all (81%). The US is also the biggest single group of patients not considering abroad – 123 of 235.
- UK patients who say no are the most worried about quality and language. 57% of them have concerns about quality of care or regulation, and 54% about language. Better information about standards abroad could change a lot of minds here – these patients aren’t worried about price at all (0%).
- Patients outside the big markets worry about cost (41%) – a reminder that IVF abroad is only “cheaper” relative to what you’d pay at home.
In patients’ own words
Some of the most honest answers came in the written comments. Patients mentioned job and business commitments, needing time off work for both partners, already having a child at home, a spouse who won’t fly, and the stress of travel.
Others had simply reached the end: “I am done doing IVF treatment.” One patient felt that, given their age, the chances of success no longer justified the travel. Another said that if they thought their clinic was the problem they might go – but they believed the problem was their eggs.
A few raised specific legal issues: rules on donor anonymity in many European countries, and whether embryos created abroad could be shipped home for future transfers. These are real, practical questions – and good clinics abroad will answer them in the first consultation.
What to do after a failed IVF cycle: practical guidance
The data shows what patients do after failure. Here’s what we’d suggest you do – based on what the patients in our survey wish had happened.
1. Insist on a proper review consultation
Don’t move straight to the next cycle. Ask for a dedicated follow-up appointment to review what happened. Some patients wait up to eight weeks for one, and contact with the clinic can stop abruptly after a negative test. Don’t accept that. Write your questions down before the appointment and bring a notebook – most people forget half of what they’re told.
A good review breaks the cycle down stage by stage: stimulation, egg collection, fertilisation, embryo development and transfer. The principle is simple. When a cycle fails, something needs to change – or the clinic needs to explain clearly why it shouldn’t.
Clues worth asking about:
- Many follicles but few eggs collected – for example, 20 follicles but only seven eggs – suggests something didn’t go well at stimulation or collection.
- Poor fertilisation – ask to speak to the embryologist. Switching from standard IVF to ICSI may help.
- Embryos that stall between day 3 and day 5 – ask about sperm DNA testing, not just egg quality.
- Repeated failure with good-quality embryos – ask about further investigations.
After repeated failure, specialists commonly consider tests such as:
- Genetic testing of embryos (PGT-A)
- Hysteroscopy (a camera check of the uterus)
- Endometrial receptivity testing (ERA)
- Tests of the uterine microbiome
- Immune and blood-clotting screening
- Thyroid function
- A full sperm work-up, including DNA fragmentation
Not every test suits every patient – immune testing after a single failed transfer, for example, usually isn’t recommended. But a clinic that won’t discuss any of them after several failures is a red flag. That’s exactly what patients in our survey described when they wrote that their doctor “insisted on using the same protocol”.
Also worth knowing: there’s no good evidence that waiting longer between cycles improves results. If you feel ready emotionally, you don’t have to wait months “to let your body recover”.
Fertility Road has a detailed guide to why IVF cycles fail and what to do next.
2. Ask the questions patients wished they’d asked
- What exactly happened at each stage – stimulation, egg collection, fertilisation, embryo development, transfer?
- How many eggs were collected, how many were mature, and how many fertilised?
- How did my embryos develop, and what grade were they?
- What do you think caused this cycle to fail?
- What will you do differently next time – and why?
- Are there tests we haven’t done that could explain this?
- What is my realistic chance of a live birth if we try again with the same approach? And with a different one?
3. Watch for the warning signs
Patients in our survey left when clinics:
- Repeated the same protocol after failure without explaining why
- Refused or didn’t offer further testing
- Didn’t follow up after a negative result
- Gave vague answers, or no data at all
- Made promises that weren’t kept
If you recognise your clinic in that list, it’s reasonable to get a second opinion. Getting one doesn’t mean leaving – it means making an informed choice.
It does work out for many patients: read real cases of IVF success after failed cycles.
4. Know when switching makes sense
Switching clinic isn’t automatically the answer. If your clinic communicates well, has a clear plan and has adjusted your treatment based on what it learned, staying may be your best option. Continuity has value.
But if you’ve had two failed cycles with no change in approach, no clear explanation and no plan, our data suggests you’re not alone in wanting to move – 71% of switchers had left by that point.
5. If you’re considering going abroad, check the things that matter
These are the same things patients rank highest when they choose an IVF clinic abroad:
- Success rates for patients like you – your age, your diagnosis, your treatment type. Not the clinic’s headline average.
- A full, itemised cost – including medication, extra embryo transfers, embryo freezing and storage, and genetic testing.
- How many trips you’ll need and how long you’ll stay.
- The law in that country – on donor anonymity, age limits, number of embryos transferred, and shipping embryos.
- Who your doctor will be – and whether they’ll speak to you before you book anything.
- Aftercare – who looks after you once you’re home, and who you call if something goes wrong.
Step-by-step help: how to choose the best IVF clinic abroad. You can also see inside clinics before you book: Behind IVF Clinic Doors is the only independent video review project for IVF clinics abroad – not based on Google reviews or star ratings.
Practical points that ease the logistics worries most patients have:
- Start with an online consultation. Most clinics abroad offer one before you travel, typically for €80–€200. You can review your history, ask your questions and meet the doctor without booking a flight.
- Expect one to two trips. Own-egg IVF usually means spending around two to four weeks near the clinic, though much of the early monitoring can often be done at home. Donor-egg treatment usually needs two trips: a short first visit of one to two days, then about a week for the transfer.
- Language is rarely a problem in practice. English is standard at the main international clinics. In IVF Media’s earlier research, only 5% of patients with previous treatment experience named a language barrier as a disappointment – far below the 34% in this survey who fear it.
- Donor waiting times are short in countries like Spain, Greece and Cyprus, where donation is anonymous. If you want an identifiable donor, check the law first – it differs by country.
- Choose a certified clinic. Standards and oversight differ between countries – especially outside the EU, where you may have no EU legal protection if something goes wrong.
The fears that stop patients – logistics, language, quality – are real. But most of them can be answered before you commit to anything.
What this means for fertility clinics
This research is written for patients first. But clinics should read it too.
The biggest finding for clinics isn’t the failure rate. It’s that patients leave over things clinics can control. Half of all switchers cited communication or the doctor relationship. One in four patients says no one warned them treatment could fail. And early leavers – the patients a clinic loses after one cycle – are almost as likely to blame communication as results.
Clinics can’t guarantee success. They can guarantee honesty about the odds, a proper review after every failure, a willingness to change course, and a doctor who explains. That’s what keeps patients – and it’s what patients are now going abroad to find.
Frequently asked questions
How many failed IVF cycles is normal?
In IVF Media’s 2025 survey of 611 patients with failed IVF, half had been through three or more failed cycles, and 34% had been through four or more. “4 or more” was the single most common answer. Repeated failure is common, especially after 40: 40% of patients aged 40–44 and 51% of patients aged 45+ had four or more failed cycles.
Should I change IVF clinic after one failed cycle?
Not automatically. One failed cycle often reflects the odds rather than a clinic problem. But it’s reasonable to consider switching if your clinic doesn’t offer a proper review, can’t explain what happened, or plans to repeat the same protocol without a reason. In our survey, 41% of patients who changed clinic did so after one failed cycle, and 71% within two.
Why do patients change IVF clinics?
In IVF Media’s survey, 57% of clinic-switchers cited a disappointing outcome, 38% poor communication, 36% their relationship with the doctor, 11% higher-than-expected costs and 9% a promise the clinic didn’t keep. Patients could choose several reasons. Half of all switchers (51%) cited communication or the doctor relationship.
How many IVF patients switch clinics?
40% of patients in IVF Media’s survey had used more than one IVF clinic. The share rises with each failed cycle – from 14% after one failed cycle to 69% after four or more.
How much do patients spend on IVF out of pocket?
47% of patients in IVF Media’s 2025 survey had spent more than €20,000 of their own money on IVF, and 57% had spent more than €15,000. Only 4% had spent nothing. Among patients with four or more failed cycles, 72% had spent over €20,000.
Which country’s patients pay the most for IVF?
US patients. 59% of US patients in IVF Media’s survey had spent more than €20,000 out of pocket – rising to 81% among fully self-funded US patients. Australia (56%), Canada (54%) and Ireland (52%) followed. UK patients spent the least of the large markets (31% over €20,000), largely thanks to NHS-funded cycles.
Do most IVF patients know treatment might fail?
Most, but not all. 74% of patients in IVF Media’s survey said their doctor explained the potential outcomes, including the risk of failure, before treatment. 26% said they were not informed. Patients who weren’t informed were more likely to switch clinic later (46% vs 39%).
Would IVF patients go abroad for treatment?
62% of patients in IVF Media’s survey would consider IVF treatment abroad. Openness is highest in Germany (80%), the UK (75%) and Ireland (73%), and lowest in the US (48%) and Australia (47%). It rises to 81% among patients aged 45 and over and 74% among patients who have already switched clinic.
What is a typical budget for IVF abroad?
56% of patients open to treatment abroad in IVF Media’s survey budget under €9,000 for treatment, excluding travel. The most common budget is €3,000–€5,000 (22% of patients). Only 10% would spend more than €20,000.
Which countries do patients travel to for IVF?
Among the 20% of surveyed patients whose last IVF cycle was abroad, the most common destinations were Greece, Spain and the Czech Republic, followed by Cyprus, Mexico, Ireland and Portugal. US patients who travelled most often chose Mexico or the Czech Republic.
What stops patients from having IVF abroad?
Travel costs and logistics (76% of patients who wouldn’t consider abroad), concerns about quality of care or regulation (36%), language and cultural differences (34%), and satisfaction with local care (32%). Only 20% cited the cost of treatment itself.
How much does one IVF cycle cost in the US, UK, Ireland, Canada, Australia and Germany?
Typical 2026 prices for one own-egg cycle: US $20,000–$25,000+ all-in; Canada up to about C$22,000 all-in; UK £5,000–£10,000; Ireland €6,000–€10,000; Australia about A$4,400–A$8,800 out of pocket after Medicare rebates; Germany about €3,000–€6,000, with statutory insurance paying 50% of three cycles for eligible married couples. Medication, freezing and embryo testing often cost extra.
How much does IVF cost abroad?
Typical base packages for own-egg IVF are €2,500–€3,500 in the Czech Republic, Greece and Northern Cyprus, €4,000–€4,600 in Portugal and €3,600–€6,700 in Spain. Donor-egg IVF typically costs €5,500–€8,500. Expect to add €1,500–€3,500 for medication and extras.
Is it worth doing IVF abroad after failed cycles at home?
For many patients, yes. In IVF Media’s survey, 20% of patients had already had their latest cycle abroad – and 96% of them would consider treatment abroad again. Patients with more failed cycles and those who’d already switched clinic were the most open to it (68% and 74%). Going abroad can mean lower costs, higher age limits, shorter donor waiting times and access to tests or protocols not offered at home.
Can I move my frozen embryos to another clinic?
Usually, yes. Frozen embryos can be shipped between clinics – including to and from other countries – with the right consent forms and a specialist transport service. Check the laws in both countries first, and ask both clinics about fees and timing before you switch.
What should I ask my clinic after a failed IVF cycle?
Ask what happened at each stage, how your eggs and embryos developed, what the clinic thinks caused the failure, what it will change next time and why, which tests could help, and what your realistic chance of a live birth is with each option. Patients in our survey often left clinics that repeated the same protocol without explanation.
Methodology
Study name: IVF Failure & Clinic Switching Survey
Conducted by: IVF Media Ltd.
Publisher: IVF Media Ltd., publisher of EggDonationFriends, FertilityClinicsAbroad and Fertility Road.
Fieldwork: 2025, online
Method: Anonymous online questionnaire, 13 questions, distributed through social media, IVF patient support groups, IVF-abroad community groups and IVF Media’s newsletter.
Responses: 638 submissions. 611 valid responses form the reporting base. 27 submissions were excluded because they answered nothing beyond the first question – including 25 respondents who reported no IVF cycles.
Respondents: patients with at least one failed IVF cycle, living in 59 countries. Largest groups: United States (236), United Kingdom (113), Ireland (40), Canada (35), Australia (32), Germany (25).
Questions covered: number of failed IVF cycles; number of clinics involved; number of failed cycles before switching clinic; reasons for switching (multiple choice plus free text); whether the patient was informed of the risk of failure; country of last treatment; age; how treatment was financed; out-of-pocket spend; country of residence; willingness to consider treatment abroad; reasons for not considering treatment abroad (multiple choice plus free text); budget for treatment abroad.
Notes on the data:
- Questions on reasons for switching were answered only by patients who had used more than one clinic (247). Questions on barriers to treatment abroad were answered only by patients who would not consider it (235). Budget questions were answered only by patients who would consider it (376).
- Multiple-choice questions allow several answers, so shares can add up to more than 100%.
- Free-text answers were grouped into themes by IVF Media’s research team. A small number of free-text answers on financing were assigned to the closest category.
- Spending and budgets were collected in euro brackets. “Median” refers to the bracket containing the middle respondent.
- Country-level results for groups under 30 respondents are marked as indicative.
- Respondents were recruited partly through IVF-abroad communities, so openness to treatment abroad may be higher than among all IVF patients. Results describe the patients surveyed and should not be read as national estimates.
Related research: This study complements IVF Media’s IVF Abroad Patient Research, a survey of 1,189 patients actively seeking IVF treatment abroad.
How to cite this research
IVF Media (2025). IVF Failure & Clinic Switching Survey – 611 patients with failed IVF cycles in 59 countries. Analysis by Aleksander Wiecki. www.ivfmedia.org/failed-ivf-clinic-switching-research/
Journalists, researchers and patient organisations are welcome to quote these findings with attribution to IVF Media and a link to this page. For additional data cuts, contact our research team.
Failed IVF: guides in other languages
Our sister sites explain what to do after a failed IVF cycle in their own languages: why cycles fail, which tests are worth asking about, and the options for your next attempt.
- Deutsch: Optionen nach gescheiterter IVF: Behandlungen und Tests (EizellspendeFreunde)
- Français : Que faire après un échec de FIV : les options (LesAmisDuDonDOvocytes)
- Italiano: Opzioni dopo una fecondazione in vitro fallita (OvodonazioneAllEstero)
Explore IVF Media’s patient research
- Seeking IVF Treatment Abroad: What 1,189 Patients Told Us – the full findings of our IVF Abroad Patient Research
- Why patients go abroad for IVF
- The most popular IVF destinations abroad – and who chooses them
- How much patients are willing to pay for IVF abroad
- How patients research IVF clinics abroad
- What makes patients choose an IVF clinic abroad
- Why Americans are travelling to Greece for IVF
About the author
Aleksander Wiecki is Chief Marketing Officer and co-founder of IVF Media Ltd. He has worked in the fertility and IVF field since 2008, leading marketing and patient experience for fertility clinics, genetic laboratories and IVF Media’s patient education websites. He is Vice-Chair of the European Fertility Society, Chair of its Cross Border Reproductive Care Committee, and a member of the European Society of Human Reproduction and Embryology (ESHRE). Aleksander leads IVF Media’s patient research programme, including the IVF Abroad Patient Research and the IVF Failure & Clinic Switching Survey.
